
Hashimoto's Disease Treatment Overview
If you have been told that your TSH is normal but you still do not feel like yourself, it can seem as if the most important part of your story has been missed. Hashimoto's involves the thyroid, but your experience can also be shaped by immune activity, medication absorption, nutrients, digestion, metabolism, sleep, stress, hormones, infections, and environmental exposures.
That does not mean every symptom comes from Hashimoto's. Fatigue, brain fog, constipation, hair changes, mood changes, muscle pain, and weight difficulty can have many causes. It means the investigation should be organized enough to distinguish thyroid hormone deficiency from the other problems that can look similar or add to it.
Job 1: restore adequate thyroid hormone
When the thyroid no longer makes enough hormone, replacement can restore the hormone your body needs. This is not simply covering up a symptom. It is replacing something the damaged gland may no longer be able to produce in sufficient amounts.
Job 2: understand your individual pattern
Investigate the triggers, drivers, physiology, diet, gut function, nutrient status, metabolism, stress, sleep, infections, exposures, medications, and life-stage changes that may be influencing immune activity and persistent symptoms.
These two jobs can happen together. Functional medicine provides a new opportunity to understand the person behind the diagnosis, while appropriate thyroid treatment protects the body from the consequences of inadequate hormone.
What Happens in Hashimoto's Autoimmune Disease?
Your immune system normally learns which proteins belong to your body and which do not. This recognition is called immune tolerance. In Hashimoto's, that tolerance is disrupted. The immune system begins reacting to proteins associated with the thyroid, most commonly thyroid peroxidase and thyroglobulin.
Thyroid peroxidase helps the gland make thyroid hormone. Thyroglobulin is a large protein used as part of that production process. Antibodies against these targets are useful clues, but antibodies are only one part of the immune response. Immune cells, inflammatory signals, oxidative stress, tissue changes, genetics, and environmental context can all influence the process.
Over time, thyroid inflammation can damage functioning tissue. The gland may compensate for a while, so antibodies can be present before TSH or free T4 becomes abnormal. If enough hormone-producing capacity is lost, hypothyroidism develops.
Hashimoto's and hypothyroidism are related, but they are not identical. Hashimoto's describes the autoimmune disease. Hypothyroidism describes inadequate thyroid hormone production or effect. Hashimoto's is a common cause of hypothyroidism, but a person can be antibody-positive before becoming hypothyroid, and hypothyroidism can occur for reasons other than Hashimoto's.
For a simple explanation of TSH, T4, T3, feedback loops, and conversion, begin with how your thyroid works. For a deeper exploration of susceptibility and immune activation, continue to Hashimoto's disease causes and triggers.
Hashimoto's Symptoms and Early Signs
There is no single symptom that proves Hashimoto's. Some people have no noticeable symptoms early in the process. When thyroid function begins to fall, the entire body can feel the effects because thyroid hormone helps regulate energy use in nearly every tissue.
The symptom pattern is often more useful than any symptom by itself. Timing matters. Did symptoms begin after pregnancy, an infection, a major stressor, a diet change, a medication change, or a period of gastrointestinal trouble? Did they improve when thyroid hormone was started and then return? Is the medication taken consistently, and could food, supplements, or digestive problems be changing absorption?
Persistent symptoms do not always mean the thyroid dose is wrong. Iron or vitamin B12 deficiency, anemia, sleep apnea, blood sugar changes, depression, menopause, medication effects, infection, celiac disease, and other autoimmune conditions can produce similar symptoms. This is why a useful plan begins by mapping the full pattern instead of automatically increasing thyroid hormone.
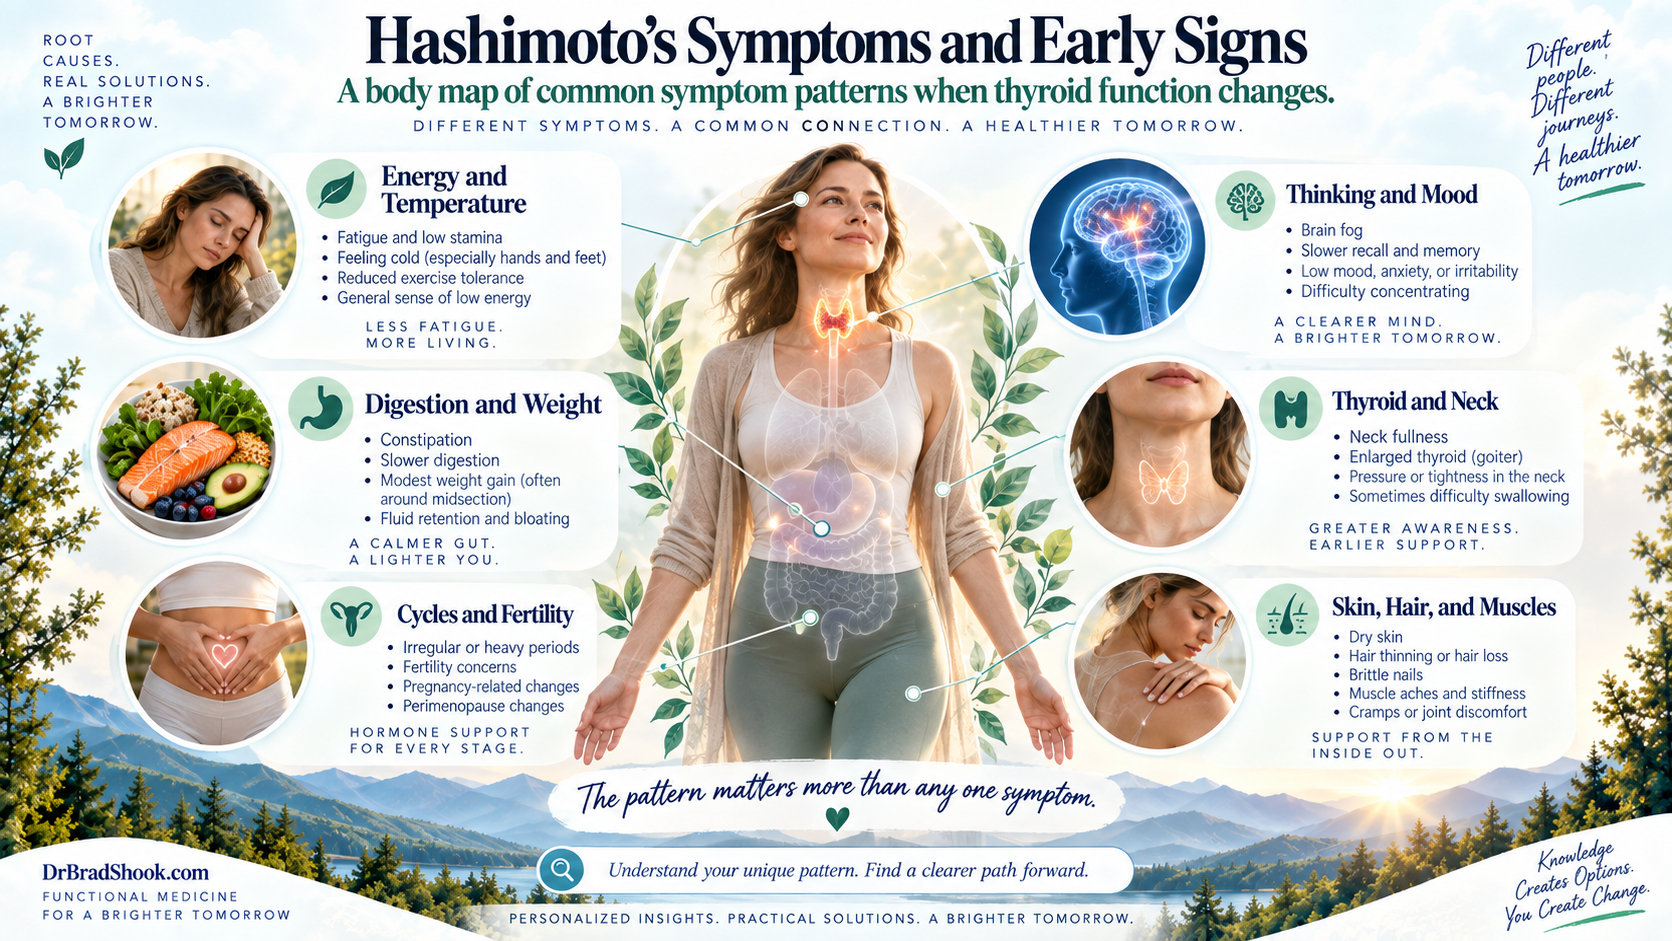
Get prompt medical evaluation for new or rapidly enlarging neck swelling, trouble breathing or swallowing, severe weakness, fainting, chest pain, a very slow or irregular heartbeat, new confusion, seizures, sudden speech or vision changes, or rapidly worsening balance or coordination. Thyroid concerns during pregnancy or while trying to conceive also deserve timely testing and follow-up.
Hashimoto's Diagnosis, Blood Testing and Thyroid Antibodies
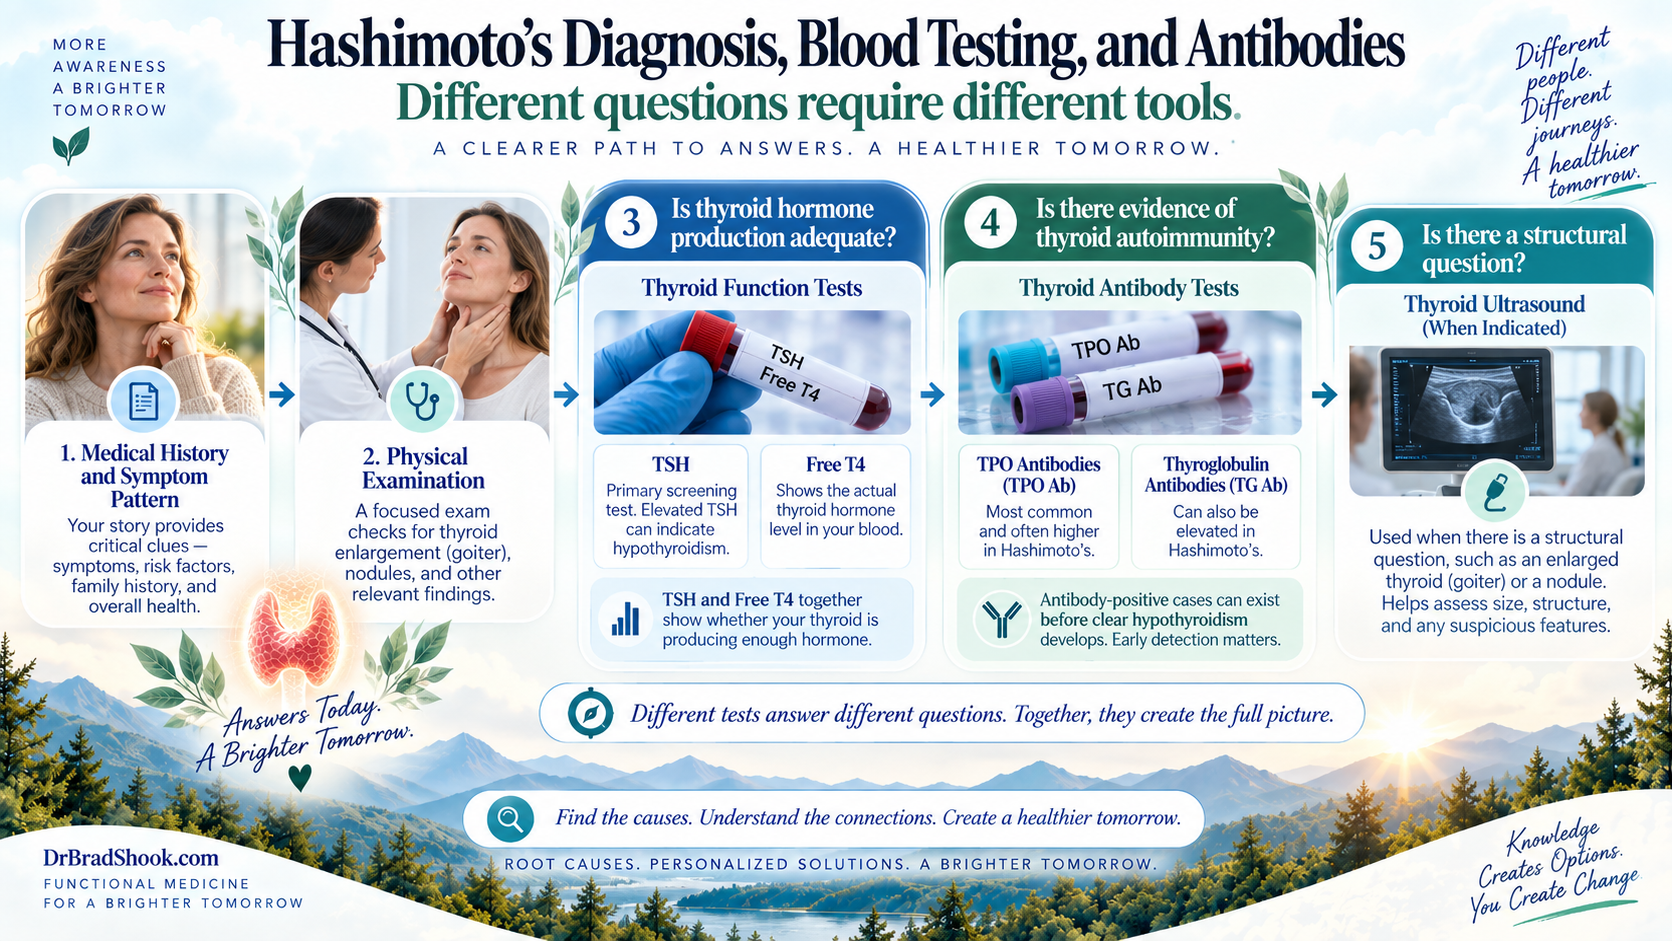
A good diagnosis separates three questions: Is the thyroid making enough hormone? Is there evidence of thyroid autoimmunity? Is there a structural problem such as enlargement or a nodule that needs imaging?
Thyroid function tests
TSH, or thyroid-stimulating hormone, reflects the signal the pituitary sends to the thyroid. Free T4 measures the available form of the main hormone released by the thyroid. These tests are commonly used together to identify and monitor hypothyroidism. Other thyroid measurements may be useful in selected situations, but a longer panel is not automatically a better panel unless the results answer a specific question.
Thyroid antibody tests
Thyroid peroxidase antibodies, often written TPO antibodies or TPOAb, are the antibodies most commonly found in Hashimoto's. Thyroglobulin antibodies, often written TgAb, may provide additional evidence. Antibodies can support the autoimmune diagnosis even while thyroid function is normal.
A positive antibody result does not tell you exactly how much functioning thyroid tissue remains, which trigger started the process, or why one person feels worse than another. Antibody levels can change, but symptoms do not always rise and fall with the number. Thyroid function, the examination, medication pattern, symptoms, and health history still matter.
Can antibodies be negative? Most people with Hashimoto's have measurable thyroid antibodies, but antibody-negative cases can occur. When the overall picture still suggests autoimmune thyroiditis, a clinician may consider the thyroid examination, ultrasound findings when appropriate, repeat testing, other causes of hypothyroidism, and the pattern over time.
Go deeper with the guides to diagnosis of Hashimoto's disease and Hashimoto's blood testing and thyroid antibodies.
Hashimoto's Ultrasound and Fine Needle Aspiration
Ultrasound shows the size and physical structure of the thyroid. It may reveal a pattern consistent with chronic thyroiditis, an enlarged or shrunken gland, or a thyroid nodule. Ultrasound does not measure thyroid hormone production and is not required for every person with Hashimoto's.
Fine needle aspiration, or FNA, is a biopsy procedure used to evaluate selected nodules based on their size, ultrasound appearance, and clinical context. FNA is not a routine test to prove that someone has Hashimoto's. It answers a structural question about a specific area of the gland.
New neck fullness, a growing lump, hoarseness, difficulty swallowing, or an abnormal thyroid examination may change the need for imaging. Learn more in the dedicated guide to Hashimoto's imaging and diagnosis.
How Hashimoto's Can Progress
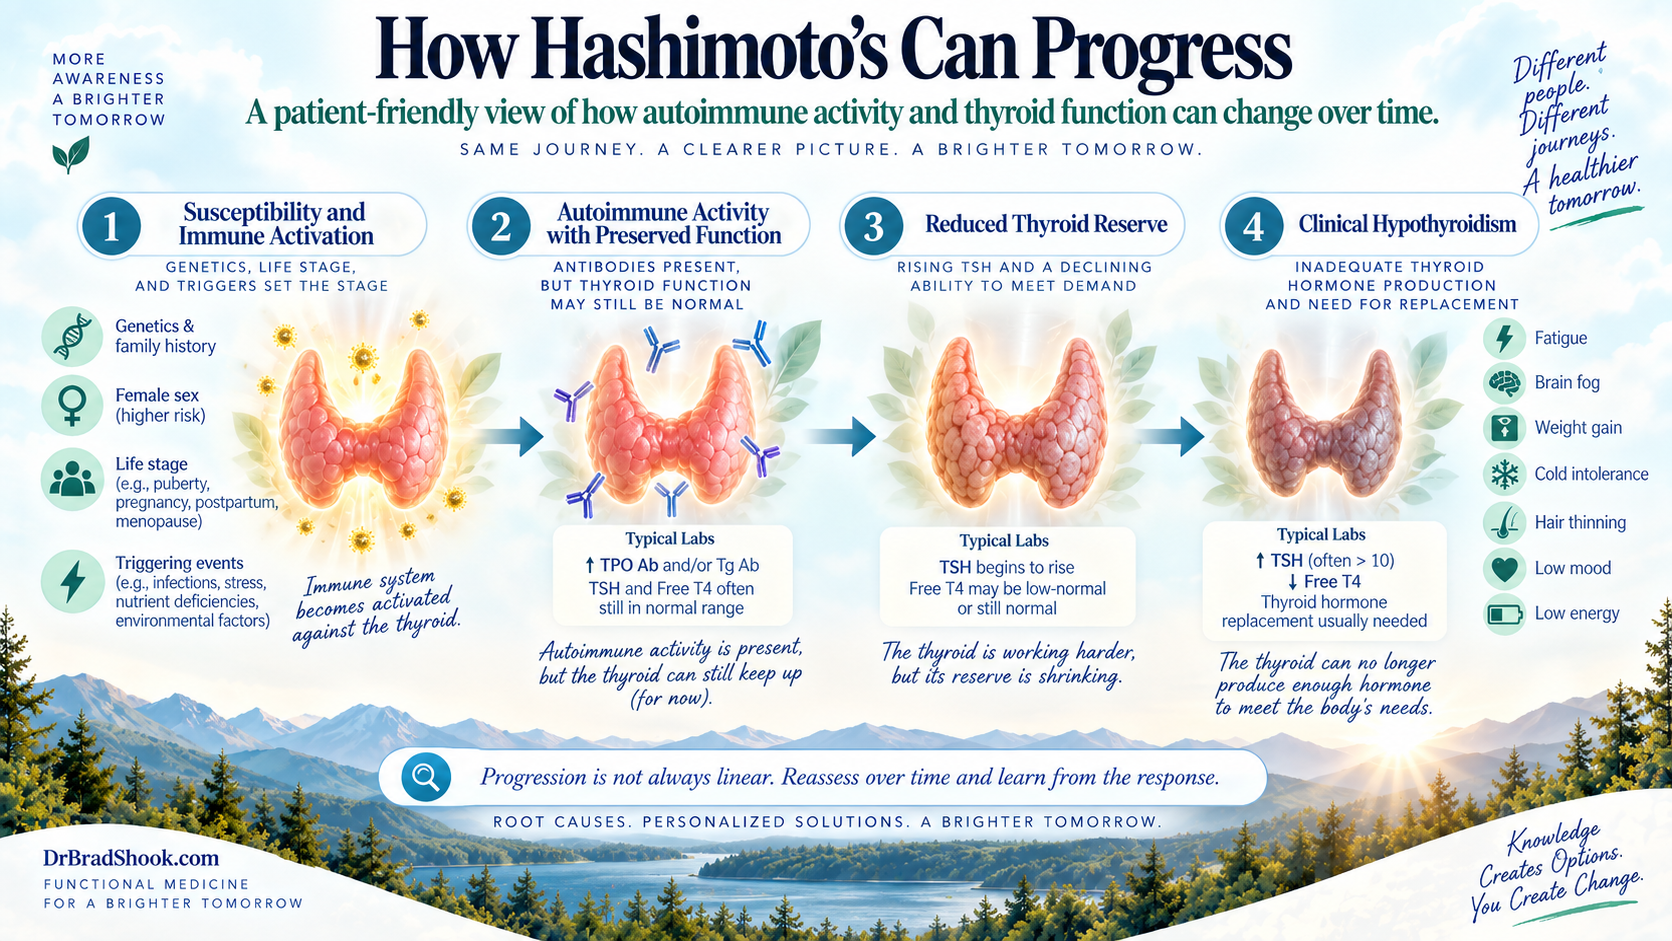
Hashimoto's does not follow one exact timeline. Some people have antibodies with normal thyroid function for years. Some develop mildly elevated TSH before free T4 falls. Others are first tested after clear hypothyroidism is already present. Thyroid inflammation can occasionally release stored hormone and create a temporary high-hormone phase, but that does not mean the gland is producing too much hormone in a stable way.
Susceptibility and immune activation
Genes, sex, family history, life stage, immune regulation, and environmental events can create the setting in which the immune system begins reacting to thyroid tissue.
Autoimmune activity with preserved function
Thyroid antibodies or tissue changes may be present while TSH and free T4 remain in range. Symptoms at this stage still require a broad differential because thyroid hormone output may be adequate.
Reduced thyroid reserve
As functioning tissue is lost, the thyroid has less ability to meet demand. TSH may rise as the pituitary asks the gland to work harder.
Clinical hypothyroidism
The gland no longer produces enough thyroid hormone. Replacement becomes an important part of treatment, while the wider autoimmune and physiological pattern can still be investigated and supported.
This is a useful educational model, not a universal staging system. People can move through it at different rates, results can fluctuate, and treatment decisions should be based on the actual laboratory and clinical picture.
Hashimoto's Treatment and Thyroid Hormone Replacement
When Hashimoto's causes hypothyroidism, thyroid hormone replacement addresses a real physiological need. The most commonly prescribed hormone is levothyroxine, a synthetic form of T4. The body can convert T4 into the active hormone T3 as needed in many tissues.
The correct dose is individual. It can change with pregnancy, major weight change, aging, gastrointestinal disease, new medications, and changes in how the medicine is taken. Follow-up commonly uses TSH and sometimes free T4, together with symptoms and the clinical situation.
Taking thyroid medication consistently
Absorption matters. Food, coffee, calcium, iron, some antacids, fiber supplements, and gastrointestinal conditions can reduce or change how much hormone enters the bloodstream. The goal is not one perfect ritual for everyone. It is a consistent routine that follows the product and prescriber's instructions, with enough separation from known interactions.
If laboratory values change unexpectedly, review how and when the medicine is taken, whether the product or dose changed, new supplements or medications, missed doses, pregnancy status, and digestive problems before assuming the thyroid itself suddenly became worse.
T3 and natural desiccated thyroid
Some patients and clinicians consider T3-containing therapy or natural desiccated thyroid, also called NDT. These products have different hormone ratios and dosing considerations than levothyroxine. They are not automatically better or more natural for every person. The decision belongs in an individualized conversation that weighs symptoms, laboratory findings, dosing stability, pregnancy status, heart and bone risks, and the ability to monitor safely.
Low-dose naltrexone and other off-label strategies
Low-dose naltrexone, often called LDN, is sometimes discussed as an off-label immune-modulating option. It is not standard thyroid hormone replacement and does not supply missing thyroid hormone. Evidence for Hashimoto's-specific outcomes remains limited, and it can interact with opioid pain medicines. Any use should be discussed with a qualified prescriber who understands the person's medications, goals, and risks.

For a closer look at medical treatment, monitoring, and medication options, visit conventional treatment for Hashimoto's. If you still feel unwell despite apparently acceptable thyroid tests, the guide to why thyroid symptoms may persist explains the next questions to investigate.
Hashimoto's Diet, Gut Health and Nutrient Status
Food is not merely a list of restrictions. It supplies the protein, fatty acids, minerals, vitamins, fiber, and energy needed for thyroid biology, immune regulation, tissue repair, metabolism, and daily function. It can also be a source of immune reactions or symptoms for an individual person.
Build the foundation before chasing a perfect diet
A useful starting point often includes enough protein and total energy, minimally processed foods, vegetables and plant variety as tolerated, healthy fats, steady meals when blood sugar is unstable, and correction of identified deficiencies. The plan should fit digestion, allergies, intolerances, preferences, culture, budget, and the person's ability to follow it.
Gluten, wheat, and celiac disease
Celiac disease and autoimmune thyroid disease occur together more often than chance alone would predict. If celiac disease is present, strict lifelong gluten avoidance is medically necessary. Outside of celiac disease, a person may still have a wheat allergy, non-celiac wheat sensitivity, another food immune reaction, or digestive symptoms associated with wheat. Those are different questions and should not be collapsed into one universal rule.
If celiac disease is suspected, testing is generally most informative while gluten is still being eaten. Learn more in the dedicated guide to gluten, celiac disease, and Hashimoto's.
The thyroid and gastrointestinal tract influence each other
Low thyroid function can slow intestinal movement and contribute to constipation. Celiac disease, autoimmune gastritis, intestinal inflammation, altered digestion, and other gastrointestinal problems can affect nutrients and medication absorption. Research has also found group-level differences in gut microbiome and barrier markers in some people with Hashimoto's, but there is no single diagnostic Hashimoto's microbiome.
Dr. Shook evaluates digestive symptoms as specific clues: bowel frequency, bloating, pain, reflux, food reactions, celiac risk, gastritis, nutrient absorption, medication absorption, infection history, and protective barrier function. That is more useful than assuming every patient has the same form of dysbiosis or that one stool result explains the thyroid.
Iodine, selenium, iron, vitamin B12, vitamin D, and zinc
Iodine and selenium are essential to thyroid physiology, but more is not always better. Excess iodine can worsen thyroid dysfunction in susceptible people, and excessive selenium can be toxic. Iron supports thyroid hormone production and oxygen delivery. Vitamin B12, vitamin D, zinc, and essential fatty acids may matter when intake, absorption, symptoms, or testing suggests a need.
Supplementation should answer a defined question. Review dietary intake, digestive health, medications, total exposure, laboratory data when appropriate, and the response after a reasonable interval. This keeps a plan individualized and reduces the chance of creating a new imbalance while trying to correct another one.

Continue to the Hashimoto's thyroiditis diet guide for a focused food strategy, or explore natural and functional treatment considerations.
The Thyroid, Brain, Gut, Liver, Metabolism and Hormones
Hashimoto's targets the thyroid, but the thyroid does not operate in isolation. Thyroid hormone affects energy use throughout the body. The immune system responds to what crosses protective barriers. The gastrointestinal tract influences digestion, nutrient and medication absorption. The liver processes hormones and chemicals. Metabolic health changes inflammatory signaling. Pregnancy, postpartum immune shifts, menstrual cycles, and menopause can change symptoms and thyroid needs.
Brain and nervous system
Thyroid hormone status, sleep, iron and vitamin B12, glucose regulation, medications, mood, inflammation, and neurological conditions can influence memory, attention, balance, nerves, and mental endurance. New neurological symptoms require their own evaluation.
Gut and protective barriers
The intestinal lining, airways, mouth, and skin help control what reaches the immune system. Celiac disease, gastritis, infections, food reactions, inflammation, oral health, and chemical exposures can provide clues about barrier stress.
Liver and metabolism
The liver participates in hormone metabolism, cholesterol regulation, glucose control, and the processing of medications and environmental chemicals. Insulin resistance, fatty liver, undernutrition, and large glucose swings can add to fatigue and inflammation.
Female endocrine system
Pregnancy, postpartum changes, fertility treatment, perimenopause, and changes in estrogen or progesterone can alter thyroid requirements, immune activity, sleep, energy, and the way symptoms are experienced.
This interconnected physiology creates a new opportunity. Instead of asking whether every symptom is thyroid or not thyroid, you can map how several systems may be influencing one another and identify which areas offer the best starting point for you.
Hashimoto's Triggers, Drivers and Functional Medicine Testing
A trigger is an event or exposure that may help activate or intensify an immune process. A driver is something that may continue influencing the pattern after it begins. Genetics, pregnancy or postpartum changes, infections, food-related immune reactions, intestinal barrier problems, medications, prolonged stress, disrupted sleep, nutrient imbalance, metabolic dysfunction, and chemical exposures may all deserve consideration when they fit the person's timeline.
No single test identifies one universal root cause. Testing becomes useful when each test answers a clear question and creates a better starting point. Depending on the pattern, an evaluation may include:
- thyroid function, thyroid antibodies, and selected imaging when a structural question is present;
- barrier-system assessment involving the gastrointestinal tract and other mucosal surfaces;
- screening for celiac disease, food immune reactions, allergy, or intolerance when supported by the history;
- targeted pathogen evaluation based on symptoms, exposures, examination, and timing;
- chemical exposure history, chemical immune-reaction questions, and selected blood or urinary exposure testing;
- vitamin, mineral, essential fatty acid, iron, and metabolic status;
- multiple tissue antibody patterns when the purpose and limits are clear; and
- lymphocyte immunophenotyping to describe patterns among immune-cell populations in selected cases.
These tests do not all mean the same thing. A positive tissue antibody does not by itself diagnose another autoimmune disease. A pathogen antibody may reflect immune memory rather than an active infection. An immune reaction to a chemical-protein complex is different from measuring the amount of that chemical in blood or urine. A barrier-associated antibody does not prove that one gut problem caused Hashimoto's.
The results become more meaningful when Dr. Shook places them beside your history, timeline, symptoms, standard laboratory results, medications, exposures, and response. That combination can produce a more individual immune and physiological fingerprint than a generic Hashimoto's checklist.

A Functional Medicine Approach to Hashimoto's
Dr. Shook's Environmentally Induced Autoimmunity model focuses on understanding what is happening beneath the diagnosis: the triggers and drivers of the immune process, the systems being affected, and the patterns that can be measured and changed.
This is not a search for one magic root cause. Hashimoto's usually develops through several interacting layers. The practical goal is to identify the most important layers in your case, support them in a logical order, and measure whether the plan is actually helping.
DETECT
Establish a baseline and identify triggers using your health history, timeline, symptoms, examination, records, and laboratory testing. Look at thyroid function, immune patterns, barrier systems, diet, nutrients, metabolism, infections, exposures, medications, stress, sleep, hormones, and the way these areas connect.
SUPPORT
Optimize diet, lifestyle, sleep, stress resilience, movement, gut function, metabolic health, and supplementation based on your triggers, findings, needs, and goals. The plan should be specific enough to follow and focused enough to show what is helping.
REASSESS
Track your energy, cognition, digestion, temperature tolerance, cycles, function, laboratory patterns, side effects, and ability to follow through with the recommended changes. Then continue what is working, adjust what is not, or stop what is unnecessary.

Explore the Hashimoto's Doctor Method, the bioindividualized systems approach, or working with a functional medicine doctor for Hashimoto's.
Where to Go Next in the Hashimoto's Learning Path
This hub is designed to give you the map. The next page should answer the most important question you have right now.
Understand causes and triggers
Learn how genetic susceptibility, acquired events, immune mechanisms, barrier systems, infections, food reactions, and exposures may interact.
Understand your diagnosis
Separate symptoms, thyroid function, antibodies, ultrasound, and biopsy so you know what each part of the evaluation can tell you.
Understand thyroid blood tests
Learn what TSH, free T4, TPO antibodies, and thyroglobulin antibodies measure and why one result rarely tells the whole story.
Understand treatment choices
Review thyroid hormone replacement, monitoring, medication absorption, diet, lifestyle, nutrients, and individualized functional strategies.
Frequently Asked Questions About Hashimoto's Disease
Is Hashimoto's disease the same as hypothyroidism?
No. Hashimoto's is an autoimmune disease that targets the thyroid. Hypothyroidism means the thyroid is not producing enough hormone, and it can have several causes. A person can have Hashimoto's antibodies while thyroid hormone production is still normal.
What are the first signs of Hashimoto's disease?
Some people have no early symptoms. When thyroid function begins to fall, possible signs include fatigue, feeling cold, constipation, dry skin, hair changes, slowed thinking, low mood, muscle aches, menstrual changes, modest weight gain, or neck fullness. These symptoms are not specific to Hashimoto's, so testing matters.
What tests are used to diagnose Hashimoto's?
Diagnosis usually combines medical history, examination, thyroid function tests such as TSH and free T4, and thyroid antibodies, most often thyroid peroxidase antibodies and sometimes thyroglobulin antibodies. Ultrasound is used when structural information is needed, not automatically for everyone.
Can you have Hashimoto's with normal thyroid antibodies?
Yes. Most people with Hashimoto's have measurable thyroid antibodies, but antibody-negative cases can occur. A clinician may use the full pattern of thyroid function, examination, imaging when appropriate, history, and follow-up rather than relying on one result.
Does everyone with Hashimoto's need thyroid medication?
Not everyone with thyroid antibodies has hypothyroidism. When Hashimoto's has reduced thyroid hormone production, thyroid hormone replacement is commonly needed, and many people require it long term. The dose and monitoring schedule should be individualized.
Can diet cure Hashimoto's disease?
No single diet has been proven to cure Hashimoto's. Food can still matter because diet influences nutrient status, metabolic health, digestion, immune exposures, and symptoms. The most useful plan is based on your diagnosis, findings, reactions, nutritional needs, and measured response.
Should everyone with Hashimoto's avoid gluten?
No. Strict gluten avoidance is necessary when celiac disease is present. Other people may have wheat-related immune reactions, allergy, intolerance, or digestive symptoms, but the decision should be individualized. If celiac disease is suspected, testing is usually most informative before removing gluten.
Can Hashimoto's affect the brain and digestive system?
Hashimoto's targets the thyroid, but thyroid hormone levels, associated autoimmunity, nutrient status, sleep, metabolism, medication absorption, and other conditions can influence thinking, mood, nerves, digestion, and bowel function. Brain or digestive symptoms should be evaluated rather than automatically blamed on Hashimoto's.
Are iodine and selenium always helpful for Hashimoto's?
No. Both nutrients are essential, but more is not always better. Excess iodine can worsen thyroid dysfunction in susceptible people, and excess selenium can be toxic. Supplementation should have a clear reason and account for diet, testing, health history, and total intake.
What does functional medicine investigate in Hashimoto's?
Functional medicine investigates the individual pattern surrounding Hashimoto's, including thyroid function, immune activity, diet, gut and barrier health, metabolism, nutrient status, stress, sleep, infections, chemical exposures, medications, hormones, and response over time. The goal is a more specific starting point, not a claim that one test reveals one universal root cause.
Ready to Understand Your Hashimoto's Pattern?
Dr. Shook uses the Environmentally Induced Autoimmunity model to investigate the connections among your thyroid, immune system, gut, brain, metabolism, hormones, diet, nutrients, stress, sleep, infections, exposures, medications, and individual response. The process is clear: DETECT what is shaping the pattern, SUPPORT the most relevant areas, and REASSESS what changes.
References and Clinical Resources
- National Institute of Diabetes and Digestive and Kidney Diseases. Hashimoto's Disease.
- National Institute of Diabetes and Digestive and Kidney Diseases. Thyroid Tests.
- American Thyroid Association. Hashimoto's Thyroiditis.
- American Thyroid Association. Thyroid Hormone Treatment.
- American Thyroid Association. Hypothyroidism in Pregnancy.
- NIH Office of Dietary Supplements. Iodine: Health Professional Fact Sheet.
- NIH Office of Dietary Supplements. Selenium: Health Professional Fact Sheet.
- Cayres LCDF, et al. Gut microbiota and intestinal permeability findings in Hashimoto thyroiditis.